Brand Name

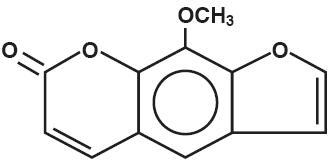
Methoxsalen

View Brand Information
FDA approval date: December 08, 2016
Classification: Photoactivated Radical Generator
Form: Capsule

What is Methoxsalen?

III. INDICATIONS AND USAGE Photochemotherapy is indicated for the symptomatic control of severe, recalcitrant, disabling psoriasis not adequately responsive to other forms of therapy and when the diagnosis has been supported by biopsy. Methoxsalen is intended to be administered only in conjunction with a schedule of controlled doses of long wave ultraviolet radiation.

Approved To Treat

Save this treatment for later
Sign Up
Not sure about your diagnosis?
Check Your Symptoms

Related Clinical Trials

THERAKOS® CELLEX Photopheresis System as an Interventional Therapy for the Treatment of Early Stage CTCL (Mycosis Fungoides), an Open-label, Single-arm, Multi-center, Phase II Study

Summary: The purpose of this study is to determine whether photopheresis therapy can be used to improve the clinical course of early stage cutaneous T-cell lymphoma (CTCL). Currently, photopheresis is performed as a palliative treatment for late stage CTCL. However, recent studies have demonstrated that patients with early stage CTCL may have markers in their blood which were previously observed primarily ...

Impact of ExtraCorporeal Phototherapy (ECP) on Auxiliary Follicular T-lymphocytes and Circulating B-lymphocytes During Chronic AntiBody-Mediated Rejection in Kidney Transplantation: IPECAM

Summary: Chronic AntiBody-Mediated Rejection (cABMR) is the leading cause of late kidney transplant loss (after 1 year of kidney transplantation). Its therapeutic management is poorly codified and there is currently no treatment referring. Extracorporeal phototherapy (ECP) is a therapeutic apheresis that involves purifying mononucleated cells in the blood, exposing them to UltraViolet A (UVA) and re-inject...

Phase 1 Study of X-PACT (X-ray Psoralen Activated Cancer Therapy) for Intra-tumoral Injection of Superficial Tumors in Patients With Advanced Head and Neck Cancer, Breast Cancer, Soft Tissue Sarcoma or Melanoma

Summary: In this Phase I trial for subjects with advanced head \& neck cancer, breast cancer, soft tissue sarcoma or melanoma all subjects will receive open label X-PACT treatment as a intra-tumoral injection. The primary objective will be to establish the safety of X-PACT when dosed with 5 intra-tumoral injections of the combination product (the phosphor device and methoxsalen sterile solution and subsequ...

Brand Information

Methoxsalen (Methoxsalen)
1I. DESCRIPTION
Methoxsalen Soft Gelatin Capsules USP contains 10mg methoxsalen. Methoxsalen occurs as white to pale yellow crystals and can be obtained naturally from seeds of
Methoxsalen
Methoxsalen Capsules are available as soft gelatin capsules containing the following inactive ingredients: Citric acid anhydrous, D & C yellow 10, FD & C blue 1, Gelatin, Glycine, Glycerin, Isopropyl alcohol, Medium chain triglyceride, Polyethylene glycol 400, Polysorbate 80, Purified water, Titanium dioxide and Opacode black.
The opacode black contains Propylene glycol, Shellac glaze (Modified) IN SD-45, N-Butyl alcohol, Black iron oxide, Isopropyl alcohol and Ammonium hydroxide.
2II. CLINICAL PHARMACOLOGY
The combination treatment regimen of psoralen (P) and ultraviolet radiation of 320-400 nm wavelength commonly referred to as UVA is known by the acronym, PUVA. Skin reactivity to UVA (320–400 nm) radiation is markedly enhanced by the ingestion of methoxsalen. In a well controlled bioavailability study, Methoxsalen Capsules, USP 10 mg [Soft Gelatin Capsules] reached peak drug levels in the blood of test subjects between 0.5 and 4 hours (Mean = 1.8 hours) as compared to between 1.5 and 6 hours (Mean = 3.0 hours) for regular hard gelatin capsule when administered with 8 ounces of milk. Peak drug levels were 2 to 3-fold greater when the overall extent of drug absorption was approximately 2-fold greater for Methoxsalen Capsules, USP 10 mg [Soft Gelatin Capsules] as compared to regular hard gelatin capsules. Detectable methoxsalen levels were observed up to 12 hours post dose. The drug half-life is approximately 2 hours. Photosensitivity studies demonstrate a shorter time of peak photosensitivity of 1.5 to 2.1 hours vs. 3.9 to 4.25 hours for regular hard gelatin capsules. In addition, the mean minimal erythema dose (MED), J/cm
Methoxsalen is reversibly bound to serum albumin and is also preferentially taken up by epidermal cells (Artuc et al., 1979
Methoxsalen acts as a photosensitizer. Administration of the drug and subsequent exposure to UVA can lead to cell injury. Orally administered methoxsalen reaches the skin via the blood and UVA penetrates well into the skin. If sufficient cell injury occurs in the skin, an inflammatory reaction occurs. The most obvious manifestation of this reaction is delayed erythema, which may not begin for several hours and peaks at 48-72 hours. The inflammation is followed, over several days to weeks, by repair which is manifested by increased melanization of the epidermis and thickening of the stratum corneum. The mechanisms of therapy are not known. In the treatment of psoriasis, the mechanism is most often assumed to be DNA photodamage and resulting decrease in cell proliferation but other vascular, leukocyte, or cell regulatory mechanisms may also be playing some role. Psoriasis is a hyperproliferative disorder and other agents known to be therapeutic for psoriasis are known to inhibit DNA synthesis.
3III. INDICATIONS AND USAGE
Photochemotherapy (Methoxsalen with long wave UVA radiation) is indicated for the symptomatic control of severe, recalcitrant, disabling psoriasis not adequately responsive to other forms of therapy and when the diagnosis has been supported by biopsy. Methoxsalen is intended to be administered only in conjunction with a schedule of controlled doses of long wave ultraviolet radiation.
4IV. CONTRAINDICATIONS
A.    Patients exhibiting idiosyncratic reactions to psoralen compounds.
B.     Patients possessing a specific history of light sensitive disease states should not initiate methoxsalen therapy except under special circumstances. Diseases associated with photosensitivity include lupus erythematosus, porphyria cutanea tarda, erythropoietic protoporphyria, variegate porphyria, xeroderma pigmentosum, and albinism.
C.     Patients with melanoma or with a history of melanoma.
D.    Patients with invasive squamous cell carcinomas.
E.     Patients with aphakia, because of the significantly increased risk of retinal damage due to the absence of lenses.
5B. INFORMATION FOR PATIENTS:
See accompanying Patient Package Insert.
6C. LABORATORY TESTS:
Patients should have an ophthalmologic examination prior to start of therapy, and thence yearly.
Patients should have routine laboratory tests prior to the start of therapy and at regular periods thereafter if patients are on extended treatments.
7D. DRUG INTERACTIONS:
See WARNINGS – GENERAL.
8E. CARCINOGENESIS:
See WARNINGS – GENERAL.
9F. PREGNANCY:
Animal reproduction studies have not been conducted with methoxsalen. It is also not known whether methoxsalen can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Methoxsalen should be given to a woman with reproductive capacity only if clearly needed.
10G. NURSING MOTHERS:
It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, either methoxsalen ingestion or nursing should be discontinued.
11H. PEDIATRIC USE:
Safety in children has not been established. Potential hazards of long-term therapy include the possibilities of carcinogenicity and cataractogenicity as described in the WARNINGS - GENERAL section as well as the probability of actinic degeneration which is also described in the WARNINGS - GENERAL Section.
12I. GERIATRIC USE:
Clinical studies with Methoxsalen Capsules, USP 10 mg [Soft Gelatin Capsules] did not include sufficient numbers of subjects aged 65 and over to determine whether elderly subjects responded differently from younger subjects. Other reported clinical experience has not identified differences in response between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
13VIII. OVERDOSAGE
In the event of methoxsalen overdosage, induce emesis and keep the patient in a darkened room for at least 24 hours. Emesis is most beneficial within the first 2 to 3 hours after ingestion of methoxsalen, since maximum blood levels are reached by this time.
14IX. DRUG DOSAGE & ADMINISTRATION
CAUTION: Methoxsalen Capsules, USP represents a new dose form of methoxsalen. This new dosage form of methoxsalen exhibits significantly greater bioavailability and earlier photosensitization onset time than previous methoxsalen dosage forms. Each patient should be evaluated by determining the minimum phototoxic dose (MPD) and phototoxic peak time after drug administration prior to onset of photochemotherapy with this dosage form. Human bioavailability studies have indicated the following drug dosage and administration directions are to be used as a guideline only.
14.1PSORIASIS THERAPY
1.    DRUG DOSAGE -INITIAL THERAPY: Methoxsalen capsules should be taken 1-1/2 to 2 hours before UVA exposure with some low-fat food or milk according to the following table:
Geriatric patients should generally be started at the low end of the dose recommended according to body weight and closely monitored during PUVA therapy. Although clinical experience has not identified differences in response between elderly and younger patients, the use of methoxsalen in older individuals may be affected by the presence of pre-existing medical conditions.
2. INITIAL EXPOSURE: The initial UVA exposure energy level and corresponding time of exposure is determined by the patient's skin characteristics for sun burning and tanning as follows:
If the MPD is done, start at 1/2 MPD.
Additional drug dosage directions are as follows:
Weight Change: In the event that the weight of a patient changes during treatment such that he/she falls into an adjacent weight range/dose category, no change in the dose of methoxsalen is usually required. If, in the physician's opinion, however, a weight change is sufficiently great to modify the drug dose, then an adjustment in the time of exposure to UVA should be made.
Dose/Week: The number of doses per week of methoxsalen capsules will be determined by the patient's schedule of UVA exposures. In no case should treatments be given more often than once every other day because the full extent of phototoxic reactions may not be evident until 48 hours after each exposure.
Dosage Increase: Dosage may be increased by 10 mg. after the 15th treatment under the conditions outlined in section XI.B.4.b.
14.2A. IRRADIANCE UNIFORMITY
The following specifications should be met with the window of the detector held in a vertical plane:
Vertical Variation: For readings taken at any point along the vertical center axis of the chamber (to within 15 cm from the top and bottom), the lowest reading should not be less than 70 % of the highest reading.
Horizontal Variation: Throughout any specific horizontal plane, the lowest reading must be at least 80 % of the highest reading, excluding the peripheral 3 cm of the patient treatment space.
14.3B. PATIENT SAFETY FEATURES:
The following safety features should be present: (1) Protection from electrical hazard: All units should be grounded and conform to applicable electrical codes. The patient or operator should not be able to touch any live electrical parts. There should be ground fault protection. (2) Protective shielding of lamps: The patient should not be able to come in contact with the bare lamps. In the event of lamp breakage, the patient should not be exposed to broken lamp components. (3) Hand rails and hand holds: Appropriate supports should be available to the patient. (4) Patient viewing window: A window which blocks UV should be provided for viewing the patient during treatment. (5) Door and latches: Patients should be able to open the door from the inside with only slight pressure to the door. (6) Non-skid floor: The floor should be of a non-skid nature. (7) Thermoregulation: Sufficient air flow should be provided for patient safety and comfort, limiting temperature within the UVA radiator cabinet to approximately less than 100 °F. (8) Timer: The irradiator should be equipped with an automatic timer which terminates the exposure at the conclusion of a pre-set time interval. (9) Patient alarm device: An alarm device within the UVA irradiator chamber should be accessible to the patient for emergency activation. (10) Danger label: The unit should have a label prominently displayed which reads as follows:
DANGER - Ultraviolet radiation - Follow your physicians instructions - Failure to use protective eyewear may result in eye injury.
14.4C. UVA EXPOSURE DOSIMETRY MEASUREMENTS:
The maximum radiant exposure or irradiance (within ±15%) of UVA (320-400 nm) delivered to the patient should be determined by using an appropriate radiometer calibrated to be read in J/cm
Exposure Time         Desired UVA Dose (J/cm
  (minutes)          =  -------------------------------------
                                   0.06 x Irradiance (mW/cm
Overexposure due to human error should be minimized by using an accurate automatic timing device, which is set by the operator and controlled by energizing and de-energizing the UVA irradiator lamp. The timing device calibration interval should be specified by the manufacturer. Safety systems should be included to minimize the possibility of delivering a UVA exposure which exceeds the prescribed dose, in the event the timer or radiometer should malfunction.
14.5D. UVA SPECTRAL OUTPUT DISTRIBUTION:
The spectral distributions of the lamps should meet the following specifications:
14.6INTRODUCTION:
The Methoxsalen Capsules, USP 10 mg [Soft Gelatin Capsules] reach their maximum bioavailability in 1-1/2 to 2 hours after ingestion.
On average, the serum level achieved with Methoxsalen Capsules, USP 10 mg [Soft Gelatin Capsules] is twice that obtained with hard gelatin capsules and reach their peak concentration in less than half the time of the hard gelatin capsules.
As a result the mean MED J/cm
Photosensitivity studies demonstrate a shorter time of peak photosensitivity of 1.5 to 2.1 hours vs. 3.9 to 4.25 hours for regular methoxsalen capsules.
14.7A. INITIAL EXPOSURE:
The initial UVA exposures should be conducted according to the guidelines presented previously under IX. Psoriasis therapy, Drug dosage-initial Therapy and initial Exposure.
14.8B. CLEARING PHASE:
Specific recommendations for patient treatment are as follows:
SKIN TYPES I, II, & III. Patients with skin types I, II, and III may be treated 2 or 3 times per week. UVA exposure may be held constant or increased by up to 1.0 J/cm
SKIN TYPES IV, V, & VI. Patients with skin types IV, V, and VI may be treated 2 or 3 times per week. UVA exposure may be held constant or increased by up to 1.5 J/cm
ERYTHRODERMIC PSORIASIS. Patients with erythrodermic psoriasis should be treated with special attention because pre-existing erythema may obscure observations of possible treatment-related phototoxic erythema. These patients may be treated 2 or 3 times per week, as a Type I patient.
MISCELLANEOUS SITUATIONS:
If there is no response after a total of 10 treatments, the exposure of UVA energy may be increased by an additional 0.5–1.0 J/cm
If there is no response, or only minimal response, after 15 treatments, the dosage of methoxsalen may be increased by 10 mg (a one-time increase in dosage). This increased dosage may be continued for the remainder of the course of treatment but should not be exceeded.
If a patient misses a treatment, the UVA exposure time of the next treatment should not be increased. If more than one treatment is missed, reduce the exposure by 0.5 J/cm
If the lower extremities are not responding as well as the rest of the body and do not show erythema, cover all other body areas and give 25 % of the present exposure dose as an additional exposure to the lower extremities. This additional exposure to the lower extremities should be terminated if erythema develops on these areas.
Non-responsive psoriasis: If a patient's generalized psoriasis is not responding, or if the condition appears to be worsening during treatment, the possibility of a generalized phototoxic reaction should be considered. This may be confirmed by the improvement of the condition following temporary discontinuance of this therapy for two weeks. If no improvement occurs during the interruption of treatment, this patient may be considered a treatment failure.
14.9C. ALTERNATIVE EXPOSURE SCHEDULE:
As an alternative to increasing the UVA exposure at each treatment, the following schedule may be followed; this schedule may reduce the total number of J/cm
Incremental increases in UVA exposure for all patients may range from 0.5 to 1.5 J/cm
Once Grade 2 clearing (see
If the rate of clearing significantly decreases, exposure dosage may be increased at each treatment (0.1-1.5 J/cm
In summary, this schedule raises slightly the increments (J/cm
14.10D. MAINTENANCE PHASE:
The goal of maintenance treatment is to keep the patient as symptom-free as possible with the least amount of UVA exposure.
SCHEDULE OF EXPOSURES: When patients have achieved 95% clearing, or Grade 4 response (Table 2), they may be placed on the following maintenance schedules (M
LENGTH OF EXPOSURE: The UVA exposure for the first maintenance treatment of any schedule (except M
If the patient develops erythema or new lesions of psoriasis, proceed as follows: a. Erythema: During maintenance therapy, the patient's tan and threshold dose for erythema may gradually decrease. If maintenance treatments produce significant erythema, the exposure to UVA should be decreased by 25% until further treatments no longer produce erythema.
b. Psoriasis: If the patient develops new areas of psoriasis during maintenance therapy (but still is classified as having a Grade 4 response), the exposure to UVA may be increased by 0.5-1.5 J/cm
FLARES DURING MAINTENANCE: If the patient flares during maintenance treatment (i.e., develops psoriasis on more than 5% of the originally involved areas of the body), this maintenance treatment schedule may be changed to the preceding maintenance or clearing schedule. The patient may be kept on his schedule until again 95 % clear. If the original maintenance treatment schedule is unable to control the psoriasis, the schedule may be changed to a more frequent regimen. If a flare occurs less than 6 weeks after the last treatment, 25 % of the maximum exposure received during the clearing phase, with the clearing schedule received during the clearing phase, may be used and then proceed with the clearing schedule previously followed for this patient. (At 95% clearing, follow regular maintenance until the optimum maintenance schedule is determined for the patient.) If more than 6 weeks have elapsed since the last treatment was given, treat patients as if they were beginning therapy insofar as exposure dosages are concerned, since their threshold for erythema may have decreased.
15XII. HOW SUPPLIED
Methoxsalen Capsules, USP 10 mg is green color, oval shaped soft gelatin capsule imprinted with 'M10' containing no drug crystals and clear colorless to pale yellow liquid, each containing 10 mg of methoxsalen (8-methoxypsoralen).  It is packed in amber colored glass bottles as 50's count (NDC 64380-752-16).
Store at 20° to 25 °C (68° to 77 °F); excursions permitted between 15 °C - 30 °C (59 °F - 86 °F).
[See USP Controlled Room Temperature]
Distributed by:
Strides Pharma, Inc.
Bridgewater, NJ 08807
16BIBLIOGRAPHY
  1. Levins, P.C., Gange, R.W., Momtaz-T,K., Parrish, J.A., and Fitzpatrick, T.B.: A New Liquid Formulation of 8-Methoxypsoralen: Bioactivity and Effect of Diet: JID,
  2. Artuc, M., Stuettgen, G., Schalla, W., Schaefer, H., and Gazith, J.: Reversible binding of 5- and 8-methoxypsoralen to human serum proteins (albumin) and to epidermis in vitro: Brit. J. Dermat.
  3. Mandula, B.B., Pathak, M.A., Nakayama, T., and Davidson, S.J.: Induction of mixed-function oxidases in mouse liver by psoralens., Ibid,
  4. Pathak, M. A., Fitzpatrick, T. B., Parrish, J. A.: PSORIASIS, Proceedings of the Second International Symposium. Edited by E.M. Farber, A.J. Cox, Yorke Medical Books, pp. 262-265 (1977).
  5. Dall'Acqua, F., Marciani, S., Ciavatta, L., Rodighiero, G.: Formation of interstrand cross-linkings in the photoreactions between furocoumarins and DNA;
  6. Cole, R. S.: Light-induced cross-linkings of DNA in the presence of a furocoumarin (psoralen), Biochem. Biophys. Acta,
  7. Musajo, L., Rodighiero, G., Caporale, G., Dall'Acqua, F., Marciani, S., Bordin, F., Baccichetti, F., Bevilacqua, R.: Photoreactions between Skin-Photosensitizing Furocoumarins and Nucleic Acids,
  8. Dall'Acqua, F., Vedaldi, D., Bordin, F., and Rodighiero, G.: New studies in the interaction between 8-methoxypsoralen and DNA
  9. Yoshikawa, K., Mori, N., Sakakibara, S., Mizuno, N., Song, P.: Photo Conjugation of 8-methoxypsoralen with Proteins; Photochem. & Photobiol.
  10. Hakim, R.D., Griffin, A.C.: Knox, J.M.: Erythema and tumor formation in methoxsalen treated mice exposed to fluorescent light; Arch. Dermatol.
  11. O'Neal, M.A., Griffin, A.C.: The Effect of Oxypsoralen upon Ultraviolet Carcinogenesis in Albino Mice, Cancer Res., 17, pp. 911-916 (1957).
  12. Stern, R.S., Unpublished personal communication.
  13. Stern, R.S., Parrish, J.A., Zierler, S.: Skin Carcinoma in Patients with Psoriasis Treated with Topical Tar and Artificial Ultraviolet Radiation. Lancet,
  14. Stern, R.S., Laird, N., Melski, J., Parrish, J.A., Fitzpatrick, T.B., Bleich, H.L.: Cutaneous Squamous-Cell Carcinoma in Patients Treated with PUVA: NEJM, 310, No. 18, pp. 1156-1161 (1984).
  15. Roenigk, Jr., H.H., and 12 Cooperating Investigators: Skin Cancer in the PUVA-48 Cooperative Study of Psoriasis. Program for Forty-First Annual Meeting for The Society of Investigative Dermatology, Inc., Sheraton Washington Hotel, Washington, D.C., May 12, 13, and 14, 1980. Abstract JID, 74 No. 4, pp. 250 (April 1980).
  16. Stern et al., Malignant melanoma in patients treated for psoriasis with methoxsalen (psoralen) and ultraviolet A radiation (PUVA). The PUVA Follow-Up Study. New England Journal of Medicine, 336:1041-1045, (April 10, 1997).
  17. Mosher, D.B., Pathak, M.A., Harris, T.J., Fitzpatrick, T.B.: Development of Cutaneous Lesions in Vitiligo During Long-Term PUVA Therapy. Program for Forty-First Annual Meeting for The Society for Investigative Dermatology, Inc., Sheraton Washington Hotel, Washington, D.C., May 12, 13, and 14, 1980. Abstracts JID,
  18. Cloud, T.M., Hakim, R., Griffin, A.C.: Photosensitization of the eye with methoxsalen. I. Acute effects; Arch. Ophthalmol.
  19. Cloud, T. M., Hakim, R., Griffin, A. C.: Photosensitization of the eye with methoxsalen. II. Chronic effects, Ibid,
  20. Freeman, R. G., Troll, D.: Photosensitization of the eye by 8-methoxypsoralen, JID,
  21. Lerman, S., Megaw, J., Willis, I.: Potential ocular complications from PUVA therapy and their prevention; JID
  22. Diffey, >L., Medical Physics Handbook 11, Ultraviolet Radiation In Medicine, Adam Hilger, Ltd., Bristol, p. 86 (1982)
Revised: 06/2026
17PRINCIPAL DISPLAY PANEL
NDC 64380-752-16
10 mg-50s-Carton-Label
10 mg-50s-Container-Label